

What Menopause Actually Does, and What Helps
Menopause is a systemic endocrine transition rather than a list of inconveniences, and the evidence about what genuinely helps has changed considerably.
Hormone Therapy
Skin & Bone
Evidence Review
By Belldiva Editorial • 2026 • 18–21 min read
Menopause is usually described as a list. Hot flashes, disturbed sleep, mood changes, dryness. Presented that way, it sounds like an inconvenient season to be endured quietly until it passes.
The physiology tells a different story. Oestrogen receptors are distributed throughout the body, in bone, brain, blood vessels, urogenital tissue, and skin. When oestrogen declines, every one of those tissues registers the change.
That is why symptoms which seem unrelated often are not. It also explains why the question of treatment matters more than the conversation around it usually allows.
This guide covers what the transition does across the body. It examines the research that shaped a generation of medical advice, and what the current evidence supports. It is longer than most of our guides because the subject deserves it.
Before We Begin
This guide discusses prescription medicine, including menopausal hormone therapy. Nothing here is a recommendation for any individual, because the risk and benefit calculation genuinely differs from one person to the next.
What we can offer is an accurate account of what the research shows, so that the conversation with your doctor starts from better information than most people currently have.

A systemic transition deserves better information than a symptom checklist.
What Menopause Does Across the Body
The clinical definition is simple. The physiological consequences reach considerably further than most descriptions suggest.
The definition, and the transition before it
Menopause itself is defined by a single marker: twelve consecutive months without menstruation. It typically occurs around the age of 51, though the range is wide and entirely normal at either end.
The years preceding it matter more than the date does. Perimenopause involves fluctuating rather than simply declining hormones. Symptoms during this phase are therefore unpredictable and hard to attribute.
Vasomotor symptoms, and how long they last
Hot flashes and night sweats are the symptoms most associated with menopause, and they are genuinely common. Data from the SWAN study found up to 80 percent of women experience them.
The duration is the part rarely mentioned. Median duration in that research was 7.4 years, and for some women symptoms persist considerably longer. Describing this as a brief phase misrepresents what many people actually experience.
Bone, and why it matters urgently
Oestrogen restrains the cells that break down bone. When it declines, that restraint lifts and bone loss accelerates sharply during the years around the transition.
This process is silent until a fracture occurs, which is precisely what makes it serious. Bone density lost during this window is difficult to recover, so prevention carries far more weight than correction.
Cardiovascular and metabolic change
Oestrogen influences blood vessel function and lipid profiles. Its decline is associated with shifts in cholesterol, blood pressure, and fat distribution toward the abdomen.
Insulin sensitivity changes too. A 2024 Menopause Society meta-analysis of 17 randomised trials examined this directly. It found hormone therapy reduced insulin resistance and prediabetes incidence.
The genitourinary syndrome, which nobody discusses
Urogenital tissue is densely populated with oestrogen receptors. Declining levels produce dryness, discomfort, urinary urgency, and increased susceptibility to infection.
Unlike hot flashes, this cluster does not resolve on its own and tends to progress without treatment. It is also among the most treatable, which makes the silence around it particularly unfortunate.
Of women experience vasomotor symptoms, according to SWAN study data
Median years those symptoms persist, which is considerably longer than most descriptions imply
Of skin collagen lost across the first five years following menopause
Oestrogen receptors sit in bone, brain, blood vessels, and skin. A decline in oestrogen is therefore never a local event.
The Study That Changed Everything, and What It Actually Found
Understanding this history is necessary, because it still shapes what women are told today.
What the Women’s Health Initiative was
The Women’s Health Initiative launched in 1991 as a major federally funded research programme. It enrolled more than 160,000 participants across randomised trials and an observational study.
Part of it tested whether hormone therapy prevented chronic disease. At the time, hormone therapy was widely prescribed for symptoms and for presumed cardiovascular protection. Those assumptions had never been rigorously tested.
When results were announced in 2002, prescribing collapsed almost overnight. Use fell dramatically across multiple countries and has never fully recovered.
The detail that changes the interpretation
Here is what the headlines omitted. The trial tested one formulation, conjugated equine oestrogen with medroxyprogesterone acetate. The average participant age was 63.
That matters enormously. Most women seeking treatment for menopausal symptoms are considerably closer to the transition itself. The trial population was, on average, more than a decade past it.
Findings from that single formulation then generated class-wide warnings. Those applied to every hormone preparation and every patient group. A result about one drug in one population became a warning about all of them.
The timing hypothesis
Subsequent reanalysis revealed a consistent pattern the original reporting obscured. Outcomes differed sharply depending on when therapy began relative to menopause.
Researchers named this the timing hypothesis, sometimes called the window of opportunity. Initiation before age 60, or within ten years of menopause, showed one profile. Initiation later showed quite another.
A narrative review in 2026 summarised the position plainly. Cardiovascular outcomes vary considerably according to formulation, route of administration, timing, and individual factors. None of that nuance survived the 2002 coverage.
What the Trial Tested vs How It Was Applied
What was studied
One oral formulation ✓
Average participant age of 63 ✓
Disease prevention as the question ✓
How it was applied
Warnings across all preparations ✗
Applied to all patient groups ✗
Used to refuse symptom treatment ✗
One formulation, tested in one population, produced warnings applied to every preparation and every woman. Two decades of caution followed from that leap.

The reanalysis took two decades to reach clinical practice, and in many places it still has not.
What the Current Evidence Supports
Professional society guidance has moved substantially. Here is where it currently stands.
Hormone therapy for symptoms
The 2022 position statement from The Menopause Society is direct. Hormone therapy is the most effective treatment available for vasomotor symptoms and for genitourinary syndrome of menopause.
It has also been shown to prevent bone loss and fracture. The United Kingdom’s NICE guidance, reviewed in late 2024, reaches broadly similar conclusions about symptom management.
Route of administration changes the risk
This distinction is clinically significant and rarely explained. Oral formulations carry an increased risk of venous thromboembolism, meaning blood clots.
Transdermal preparations behave differently. A 2026 review notes that transdermal estradiol with micronised progesterone does not appear to increase that risk. It bypasses first-pass liver metabolism.
Transdermal delivery also appears particularly favourable for women with existing metabolic risk factors. Anyone weighing this decision should ask specifically about route rather than treating hormone therapy as a single choice.
Where the guidance still holds firm
Balance requires stating this clearly. Major medical societies do not recommend hormone therapy for preventing chronic disease. The United States Preventive Services Task Force reaffirmed that position in 2022.
The distinction is between treating symptoms and preventing future illness. Evidence supports the first far more strongly than the second. Reading the reappraisal as a blanket endorsement would be a mistake.
A genuine caution from recent practice
Honesty requires including this alongside the rest. A review in Clinical Endocrinology tracked what followed rising prescriptions. Unscheduled bleeding on hormone therapy rose roughly 43 percent in the United Kingdom between 2021 and 2024.
Referrals for suspected cancer rose correspondingly, and endometrial cancer diagnoses increased by 2 percent over the same period. The review observes that women accessing therapy in practice differ from trial participants, often carrying more coexisting conditions.
None of that argues against treatment. It argues for proper monitoring. Report any unexpected bleeding promptly rather than assuming it is part of the process.
What the Evidence Supports vs What It Does Not
Well supported
Hormone therapy for vasomotor symptoms
Local treatment for urogenital symptoms
Prevention of bone loss and fracture
Not currently recommended
Hormone therapy to prevent chronic disease
Compounded bioidentical preparations
Treating without individual risk assessment
The reappraisal corrected an overcorrection. It did not turn hormone therapy into something everyone should take.
Non-Hormonal Options That Genuinely Work
Hormone therapy is not suitable or desirable for everyone, and the alternatives have improved considerably.
A genuinely new class of medication
Fezolinetant represents the first meaningful non-hormonal advance in this area for some time. It works by blocking neurokinin 3 receptors in the brain region governing temperature regulation.
The trial data is strong. A phase 2b study enrolled 352 participants. Between 81 and 95 percent achieved at least a halving of symptoms. Placebo managed 58.5 percent.
An earlier proof of concept study found symptom frequency fell roughly 88 to 93 percent from baseline. Placebo produced 38 to 46 percent. Effects appeared within the first week of treatment.
Other prescription routes
Certain antidepressants have established evidence for reducing vasomotor symptoms, at doses lower than those used for mood. Other medications originally developed for different purposes also feature in current guidance.
Local vaginal oestrogen deserves separate mention. Absorption into the bloodstream is minimal, so it often suits women who cannot use systemic therapy. It treats the urogenital symptoms that otherwise progress.
The treatment gap
One figure captures the scale of the problem. A retrospective study reviewed records of 1,016 women presenting with menopausal symptoms, the overwhelming majority reporting hot flashes.
Nearly 40 percent had no documentation of any prescription therapy being offered. Thirteen percent had no therapy of any kind recorded, including non-prescription options and lifestyle advice.
Those women attended appointments and described their symptoms. The system then offered them nothing at all.
Of women presenting with symptoms had no prescription therapy documented as offered
Received nothing at all, including lifestyle advice or non-prescription suggestions
Randomised trials pooled in the 2024 meta-analysis examining metabolic outcomes
Nearly four in ten women who described their symptoms to a clinician had no treatment of any kind offered in response.
What Menopause Does to Skin and Hair
This receives far less attention than vasomotor symptoms, despite affecting quality of life considerably.
The collagen figure, and what it means
Skin functions as an endocrine organ and responds directly to oestrogen. Research published in Climacteric reports a collagen reduction of approximately 30 percent across the first five years following menopause.
A further decline of roughly 2 percent annually follows for the next fifteen years. Crucially, that loss correlates more closely with duration of oestrogen deficiency than with chronological age.
This explains something many women describe and are rarely believed about. Skin can change noticeably within a relatively short period, and the perception of a sudden shift is not imagined.
What hormone therapy does to skin, honestly
Oestrogen replacement has been shown to increase epidermal thickness and skin collagen content. One study recorded a 6.49 percent increase in skin collagen following six months of oral oestrogen.
Effect sizes are modest, though, and largely apply to therapy begun in the early post-menopausal window. The honest framing is that it slows loss and partially restores thickness. It does not return skin to its previous state.
Skin benefit alone is not a reason to begin hormone therapy, and no guideline suggests otherwise. It is better understood as a welcome effect for women taking it for other reasons.
Topical care that remains worthwhile
Retinoids and daily sun protection retain their strong evidence regardless of hormonal status. Barrier support becomes more important as skin thins and dryness increases.
The Belldiva skin barrier repair guide covers what supports that layer. Our hormone skincare routine guide addresses the adjustments worth making.
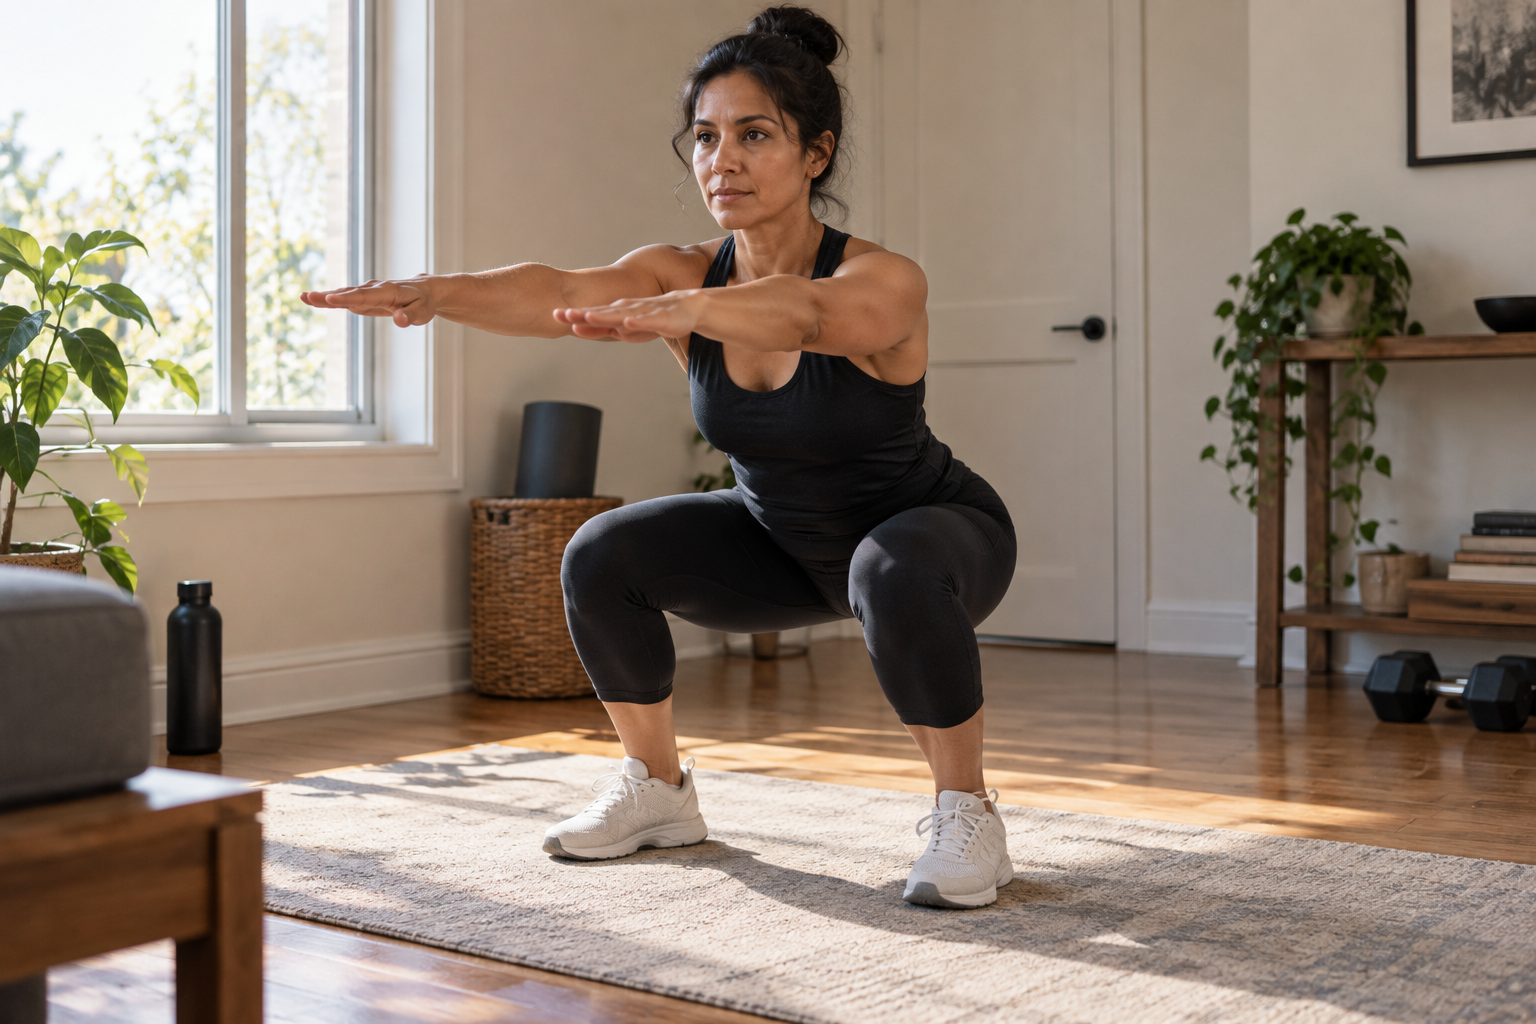
Resistance training is among the few interventions that addresses bone, muscle, and metabolic change simultaneously.
What Else Genuinely Helps
These carry real evidence, and one of them addresses several systems at once.
✦
Resistance training, which does the most work
Loading bone stimulates the cells that build it, directly countering accelerated bone loss. It also preserves muscle mass and supports insulin sensitivity. Our muscle memory guide covers why returning to training is easier than starting fresh.
✦
Protein and calcium intake
Muscle preservation requires adequate protein, and bone requires calcium alongside vitamin D. Requirements often rise during this period while appetite and habits stay the same. Worth discussing specifics with your doctor rather than guessing.
✦
Sleep, treated as a priority
Night sweats disrupt sleep, and poor sleep worsens mood, cognition, and metabolic markers. Breaking that loop often improves several symptoms simultaneously. Treating the vasomotor symptoms directly is frequently the most effective route.
✦
A clinician who knows this field
Menopause training has been thin in medical education for decades, and knowledge varies enormously between practitioners. If you are dismissed or told to simply wait it out, seeking another opinion is reasonable rather than difficult.
On the supplement aisle
The market for menopause supplements is enormous and the evidence behind most of it is thin. Black cohosh, evening primrose, and various botanical blends have been studied repeatedly with inconsistent results.
That does not make them harmful, and some women report benefit. It does mean the packaging claims exceed what the trials support. Spending there while effective prescription options go unoffered is a poor trade.
Wealth without wellness is incomplete, and no woman should spend this transition being told that what she is experiencing is simply to be endured.
Common Questions About Menopause
Direct answers to what comes up most, with the caveat that individual decisions belong with your doctor.
Questions about hormone therapy
Is hormone therapy safe?
That question has no single answer. Risk depends on your history, the formulation, the route, and when you begin relative to menopause. For many healthy women within ten years of the transition, current guidance considers it safe and effective for symptoms. The assessment has to be individual.
What about the breast cancer risk I have heard about?
Risk varies by formulation and duration, and it is a genuine consideration rather than a myth. What changed is the recognition that the original warnings were applied far more broadly than the underlying data justified. Your doctor can weigh this against your own history properly.
Questions about timing and alternatives
Have I missed the window?
Current guidance generally favours initiation before age 60 or within ten years of menopause. That said, a 2024 paper in The Lancet Diabetes and Endocrinology questioned those limits. They exclude women with genuine symptoms. Worth raising directly with a clinician.
What if I cannot take hormones?
Non-hormonal prescription options exist and have improved considerably, including newer medications targeting temperature regulation directly. Local vaginal oestrogen is often suitable even when systemic therapy is not, because absorption is minimal. Ask specifically about both.
Sources and research references
The 2022 hormone therapy position statement of The North American Menopause Society. Menopause. 2022;29:767-794 | National Institute for Health and Care Excellence. NG23 Menopause: identification and management. Reviewed November 2024 | US Preventive Services Task Force. Hormone Therapy for the Primary Prevention of Chronic Conditions in Postmenopausal Persons. JAMA. 2022;328(17):1740-1746
Manson JE, Chlebowski RT, Stefanick ML, et al. Menopausal hormone therapy and health outcomes during the intervention and extended poststopping phases of the Women’s Health Initiative randomized trials. JAMA. 2013;310:1353-1368 | Chlebowski RT, Anderson GL, Aragaki AK, et al. Association of Menopausal Hormone Therapy With Breast Cancer Incidence and Mortality During Long-Term Follow-Up of the Women’s Health Initiative Randomized Clinical Trials. JAMA. 2020;324(4) | Taylor S, Davis SR. Is it time to revisit the recommendations for initiation of menopausal hormone therapy? Lancet Diabetes Endocrinol. 2024;13(1):69-74
The impact of hormone replacement therapy on cardiovascular health in postmenopausal women: a narrative review | Mukherjee et al. Update on Menopause Hormone Therapy: Current Indications and Unanswered Questions. Clinical Endocrinology. 2025 | Then and Now: What We Have Learned From the WHI
A phase 2b, randomized, placebo-controlled, double-blind, dose-ranging study of the neurokinin 3 receptor antagonist fezolinetant for vasomotor symptoms associated with menopause. Menopause (n=352) | Skin, hair and beyond: the impact of menopause. Climacteric. 2022 | Managing Menopausal Skin: A Clinician’s Review. European Medical Journal. 2025
The information in this guide is for educational purposes and reflects research current to mid-2026. It does not constitute medical advice. The prescription treatments discussed require assessment by a qualified clinician who knows your history. Please report any unexpected bleeding to your doctor promptly.
Rooted in Care. Refined in You.
Explore Belldiva’s Curated Collection
Over 70 luxury brands across skincare, wellness, and movement. Every brand chosen for genuine excellence and real results.
Belldiva’s Curated Beauty and Wellness Brands
All Belldiva Brands
Huda Beauty
Charlotte Tilbury
Sephora
MAC
Dior
Katini Skin
Ultra Violette
NYX Cosmetics
The Ordinary
Verb Products
BK Beauty
Prada Beauty
Estée Lauder
Vasanti Cosmetics
Brickell
Lumin
Blu Atlas
Liomen
Jaxon Lane
Beardbrand
Scotch Porter
Bevel
Menfirst
Atlas
SkinCeuticals
Lululemon
Mindful
Headspace
Calm
Fitbit
MyFitnessPal
Noom
Peloton App
Organifi
Ritual
HUM Nutrition
Nike
YSL (Saint Laurent Beauty)
Lancôme
Clinique
NARS
Elizabeth Arden ✦
Victoria Beckham Beauty
Make Up For Ever
Valentino Beauty
Bobbi Brown
Shiseido
Benefit Cosmetics
Smashbox
Kylie Cosmetics
Urban Decay
Sigma Beauty
Stila ✦
Clarins
Tarte Cosmetics
PUR Cosmetics
Glossier
Elemis London
Kiehl’s
Murad
Paula’s Choice
Viori Beauty ✦
Life Extension
Lumen
Fiji Water
Anastasia Beverly Hills
Serious Skincare
Qure Skincare
Armani Beauty
Dr. Brandt ✦
menopause
hormone therapy
perimenopause
bone health
collagen
women’s health
hot flashes
Belldiva wellness